
           CASE E-LOG                      

                                                CASE SHEET

           A 70 year old female came with c/o SOB since 7 days  

Chief complaints:    

  • shortness of breath with cough
History of presenting illness:
  • Patient was apparently asymptomatic 2 years back. The patient then had an episode of SOB . Now, the patient again has an episode of SOB  associated with cough with expectoration , scanty sputum present .No h/o pedal edema , decreased urine output, hematuria, frothy urine.

History of past illness:
  • 2 years back patient had similar complaint of shortness of breath and treated in a local hospital.
Family history :
  • No relevant family history.
Personal history 
  • Diet :                              Mixed
  • Appetite :                      decreased
  • Bowel movements :      Regular
  • Bladder movements :     Regular
General examination:

         Patient is conscious, coherent and cooperative
         Malnutrition+ ,mild dehydration
  • Pallor: - Not seen
  • Icterus: - Not seen
  • Cyanosis: - Not seen
  • Clubbing: - Not seen
  • Koilonychia: - Not seen
  • Lymphadenopathy: - Not seen
  • Edema: - Not seen


VITALS : 
  •  Temp: 98.7 F 
  • PR: 60 bpm 
  • BP: 110/70 mm hg 
  • RR: 18 cpm 
  • Spo2 - 98%
CVS : S1, S2 heard , No murmurs


RS : 
  • Position of trachea: central 
  • Dyspnea +
  •  Wheeze +
  •  BAE present decreased in rt side 
  • Expiratory wheeze + on rt IMA,ISR,IAA 
  • B/L Inspiratory crepts + in ISA +,IAA +


PER ABDOMEN: Soft, non tender
  • Bowel sounds +


CNS: 

  • Patient is Conscious ,oriented to time,place and person 
  • HMF -intact
  •  Motor & sensory system: normal 
  • Reflexes: present
  •  Cranial nerves: intact 
  • No meningeal signs
PROVISIONAL DIAGNOSIS- ?AKI WITH COPD

INVESTIGATIONS :     
                                                    URINARY SODIUM 


ULTRASOUND


LIVER  FUNCTION  TEST


SERUM  ELECTROLYTES
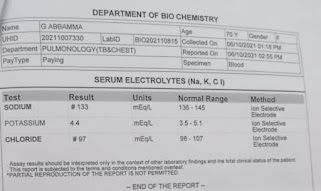

SERUM CREATININE


COMPLETE  URINE  EXAMINATION


                                                                   HEMOGRAM  

ERYTHROCYTE  SEDIMENTATION RATE


                                            URINE PROTEIN/ CREATININE RATIO


Day 1 soap notes : 
S : SOB decreased 
O  : O/E
       Pt is C/C/C 
       Temp : afebrile 
       BP : 
       PR :
       CVS :S1S2 +
       RS : BAE +
      Tubular sounds + at rt IMA, ISA 
       P/A : soft , NT
       CNS : : no focal deficit 
 A : ? PRE RENAL AkI with COPD 
 P : 
     1. IVF :NS,RL @ 50 ml / HR 
     2. Inj. Augmentin 2 GM IV BD
     3. Inj . Pan 40 mg IV OD BBF 
     4. TAB. DOLO 650 MG OD SOS 
     5. SYP. ASCORIL.10 ML PO/ BAD 
     6. NEBULISATION WITH 
          Duolin- 8 the hourly 
          BuDicort -17 th hourly
          Furacort - 8 th hourly 
    7. BP charting 8 th hourly


Comments

Popular posts from this blog

A case of a 78 yr old female with altered sensorium

My patient is a 78 year old  female housewife hailing from a rural district in south india. She presented to us with chief complaints of : Patient was brought to casuality on 23/11/22 at 4:00 am early  in the morning with complaints of loose stools since 5 days and pain as mentioned by the atttender as she was screaming and restless with altered sensorium. History of presenting illness : The patient was apparently asymptomatic 5 days ago. She passed loose stools- watery in consistency, foul smelling and blood tinged on consuming kaya churnam (an ayurvedic powder) , went to RMP nearby and was given medication,  even upon which loose stools didnot stop . The attender mentions she became weak and then on 23rd nov, apparently after eating curd rice ,  when patient slept , suddenly in the middle of night patient was screaming due to pain  and could not talk anything, as mentioned by the attender. She was then bought to casuality. History of past illness: The patient'...

24

 Case History and Clinical Findings 43 YEAR OLD FEMALE PATIENT CAME WITH COMPLAINTS OF FEVER SINCE 1 WEEK, VOMITINGS AND LOOSE STOOLS SINCE 4 DAYS INVOLUNTARY MOVEMENTSOF BOTH UPPER LIMBS AND LOWER LIMBS SINCE 1 DASY HOPI: PATIENT WAS APPARENTL ASYMPTOMATIC 1WEEK BACK, THEN SHE DEVELOPED FEVER OF LOW GRADE INTERMITTENT, RELIEVED ON MEDICATION NOT ASSOCIATED WITH CHILLS AND RIGOR, BURNING MICTURITION, COUGH AND COLD PATIENT HAD VOMITINGS WHICH ARE BILIOUS, NON PROJECTILE, NON BLOOS TINGED, FILLED WITH FOOD PARTICLES(2-3 TIMES PER DAY)     C/O LOOSE STOOLS LOW VOLUME, WATERY CONSISTENCY, NON MCOPURUENT, NON BLOOD TINGED, NO H/O OUTSIDE FOOD CONSUMPTION PATIENT HAD 3 EPISODES OF INVOLUNTARY MOVEMENTS 9RIGIDITY OF BOTH UPPER LIMBS AD LOWER LIMBS) ASSOCIATED WITH UPROLLING OF EYES, INVOLUNTARY MICTURITION, TONGUE BITE AND IS IN POST ICTAL CONFUSION/IRRITABLE SINCE THEN PAST HISTORY: K/C/O HTN SINCE 3 MONTHS(ON IRREGULAR MEDICATION OF UNKNOWN DRUGS) NOT A K/C/O DM, ASTHMA,...

OSCE PREFINAL EXAM

 OSCE- PREFINALS DEC 2023: Case report :    I have tried to answer some of the questions regarding case discussion of our patient    1. How to clinically differentiate between coarse and fine crepitations ? Ans-  well, crepitations or crackles  are adventitious respiratory sounds which occur when an obstructed airway due to accumulated  secretions opens in inspiratory phase. The sudden opening of an obstructed airway causes an immediate re-equilibration of the pressures on both sides creating vibrations in the airway walls.  Fine crackles --  A).  having a short duration and a higher pitch,           Often, fine crackles are repetitive, originate          in the basal part of the lung, and not altered          by coughing. B) Coarse crackles  appear to be a longer                     durati...